Most cardiovascular events come after the first 100 days
Most patients get through the transplant itself. Their cardiovascular risk is concentrated in the months and years after it, later than people expect.
In our registry of 3,354 adults transplanted at two centers, the cumulative incidence of cardiovascular events was 4.1% at 100 days and 13.9% at five years [1]. Events were a composite of cardiovascular death, myocardial infarction, heart failure, atrial fibrillation or flutter, stroke and sustained ventricular tachycardia. Atrial fibrillation or flutter was the commonest event at both time points (2.6% and 6.8%), followed by heart failure (1.1% and 5.4%). Allogeneic recipients had a higher five-year incidence than autologous recipients, 16.4% against 12.1%.
The short-term rate is lower than the procedure's reputation suggests, and the five-year rate is roughly three times as high. A cardiology assessment focused only on surviving the first hundred days misses most of the events.
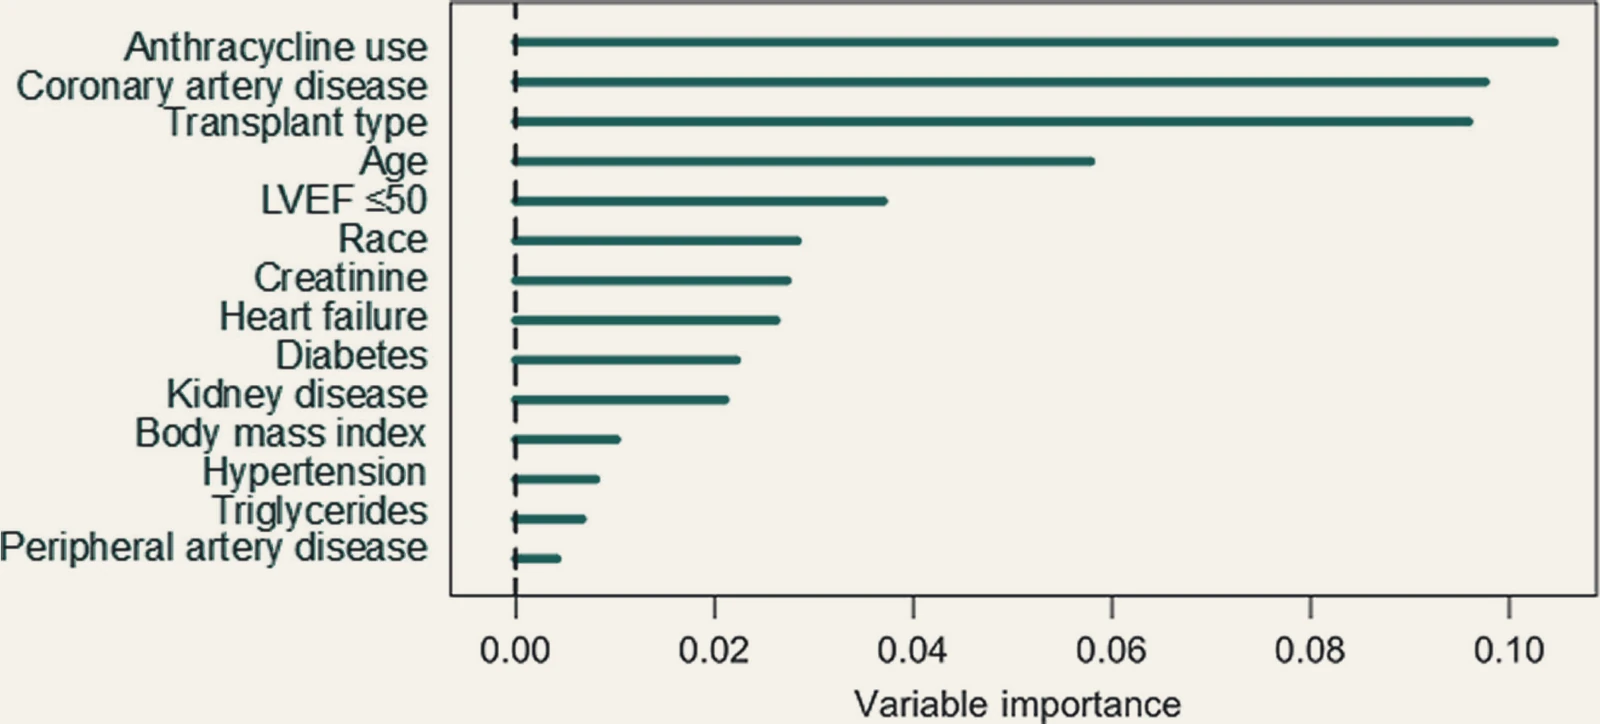
Prior anthracycline exposure, coronary artery disease and transplant type predicted these events more strongly than most traditional cardiovascular risk factors [2].
Cellular therapies given by the same service follow a different time course. After chimeric antigen receptor (CAR) T-cell infusion, cardiac injury occurs within days and tracks the severity of cytokine release syndrome, not a cumulative dose [3]. The rest of this page concerns transplantation itself.
A score identifies high-risk patients before transplant
Identifying risk before treatment starts leaves time to prepare the patient for it.
We derived the CARE-BMT score in 2,435 transplant recipients and validated it externally in a separate cohort of 919 [2]. It uses age, transplant type, race, coronary artery disease, heart failure, peripheral artery disease, creatinine, triglycerides and cumulative anthracycline dose, all available before the transplant decision.
In the derivation cohort, the five-year cumulative incidence of cardiovascular events was 4.0%, 10.3% and 22.4% in the low-, intermediate- and high-risk groups [2]. Areas under the curve, accounting for the competing risk of noncardiovascular death, were 0.65 (95% CI 0.59–0.70) at 100 days, 0.73 (95% CI 0.69–0.76) at five years and 0.76 (95% CI 0.69–0.81) at ten years. Performance was similar in autologous and allogeneic recipients. In the external validation cohort, the five-year area under the curve was 0.68 (95% CI 0.63–0.74). The score is intended to identify candidates for cardiology referral before transplant and to set the intensity of long-term monitoring. It does not mark anyone to be turned away.
Ejection fraction alone should not rule out a transplant
Ejection fraction is the number most often used to refuse a transplant, yet it has the least evidence behind it for that use.
The 2024 American Heart Association statement, which we led, says a transplant should be refused on cardiovascular grounds only for the occasional patient with severe untreatable disease, poor cardiopulmonary reserve, or a life expectancy under a year [4]. We had put it more bluntly three years earlier: patients with a left ventricular ejection fraction below 35% are often denied a transplant, and the data do not support the practice [5].
The evidence behind that position comes from other groups and is consistent. No guideline sets an ejection fraction threshold. The comorbidity index most often cited in these decisions was derived in allogeneic recipients to predict nonrelapse mortality and survival, with no cardiovascular end point. Its cardiac item combines coronary artery disease, heart failure, prior myocardial infarction and reduced ejection fraction, and carries a low weight [6]. Two single-center studies comparing recipients with a reduced ejection fraction against matched recipients with a preserved one found similar rates of cardiac complications and of 100-day nonrelapse mortality [7, 8].
One recent cohort points the other way: among 852 allogeneic recipients, a pre-transplant ejection fraction below 50% was independently associated with cardiovascular events within 100 days (subdistribution HR 3.16, 95% CI 1.43–6.98) [9]. Every reassuring study is retrospective and subject to referral bias, since the sickest candidates were never referred. No one has run a randomized trial.
None of this argues for a new cutoff. Our own score, derived for cardiovascular events specifically, assigns no points to ejection fraction. In the multivariable model behind it, an ejection fraction below 50% had a hazard ratio of 1.15 (95% CI 0.60–2.19), and the largest weights went to age, allogeneic transplant and prior anthracycline dose [2]. A patient with a reduced ejection fraction carries a risk that can be estimated, managed in the weeks before conditioning (the chemotherapy, with or without total body irradiation, given before the cells are infused), and monitored closely afterwards. The choice is rarely between transplanting and not; it is between transplanting a patient who has been prepared and one who has not.
Atrial fibrillation after transplant is a warning sign
Atrial fibrillation after transplantation is usually treated as a transient periprocedural complication. Its association with later mortality does not fit that view.
In our registry, atrial fibrillation or flutter was the commonest cardiovascular event at both 100 days and five years [1].
In a single-center retrospective cohort of 801 patients with multiple myeloma undergoing autologous transplantation, 8.7% developed atrial fibrillation, at a median of 13 days. Age over 65, obesity and a history of paroxysmal atrial fibrillation were independent predictors. After multivariable adjustment, its onset was associated with all-cause mortality (HR 5.05, 95% CI 3.05–8.37) and with nonrelapse mortality (HR 4.53, 95% CI 1.43–14.3) [10].
The nonrelapse estimate rests on only 32 deaths, but it is the more specific of the two, because it excludes deaths from myeloma progression. An arrhythmia usually regarded as transient should not remain associated with death years later unless it marks something lasting about the patient. We have argued that post-transplant atrial fibrillation is best read as a sentinel of limited cardiovascular and systemic reserve [11]. On that reading, its onset calls for a full evaluation of the patient in addition to rate control.
A diabetes drug class offers the first prevention signal
Identifying who is at risk helps only if something can be done about it. That part of the program is still open.
The most promising signal so far comes from a drug class developed for glycemic control. In our analysis of 11,682 transplant recipients with diabetes in the TriNetX health-record network, the 12% taking a sodium-glucose cotransporter 2 inhibitor had about half the odds of death at five years compared with propensity-matched non-users (OR 0.49, 95% CI 0.40–0.60). Users also had lower odds of hospitalization and of heart failure exacerbation [12].
An association that large in an observational study warrants caution: patients well enough to be started on a new drug differ from those who are not, and propensity matching cannot fully remove that healthy-user bias. The result justifies a randomized trial and cannot stand in for one. The 2024 American Heart Association statement set out the pathway from pre-transplant assessment to long-term survivorship, and marked which parts rest on evidence and which on consensus [4].
Read next: